On this page
When a doctor pumps up the cuff on your arm and listens with a stethoscope, they are waiting for sounds first described in a one-page report in St Petersburg in 1905. Before then, doctors could measure the top number of blood pressure with a cuff but had no easy way to get the bottom one. This post covers Nikolai Korotkov, the problem he was actually trying to solve, what he heard, and how to read a blood pressure measurement step by step.
His name appears in English both as Korotkov and as Korotkoff; they are the same person.
Who was Nikolai Korotkov?
A 2005 centenary tribute in Kidney and Blood Pressure Research records that he was born on 26 February 1874 in Kursk, in central Russia, graduated from the medical faculty of Moscow University in 1898 and later worked in the surgical clinic of the Imperial Military Medical Academy in St Petersburg. He served as a military surgeon in the Russo-Japanese War of 1904 to 1905. He died in 1920.
A 2016 paper in the Journal of Trauma and Acute Care Surgery, written partly by surgeons at the same Military Medical Academy, describes him as one of the first military vascular surgeons to study wounded arteries carefully, on voluntary trips to the Russian Far East in 1900 to 1901 and during the war.
What problem was he trying to solve?
Korotkov was not a blood pressure researcher. As Estañol, Delgado and Borgstein explain in Arquivos Brasileiros de Cardiologia, his concern as a war surgeon was whether a limb with a wounded artery had enough blood supply from side branches. If it did, the damaged artery could be tied off safely; if not, amputation might follow.
Riva-Rocci's cuff already existed. Our post on Scipione Riva-Rocci and the cuff explains how it measured systolic pressure by touch: inflate until the wrist pulse vanishes. But touch could not reliably find the diastolic pressure. Estañol and colleagues note that many physiologists had searched for a non-invasive way to measure it, without success.
What did he hear?
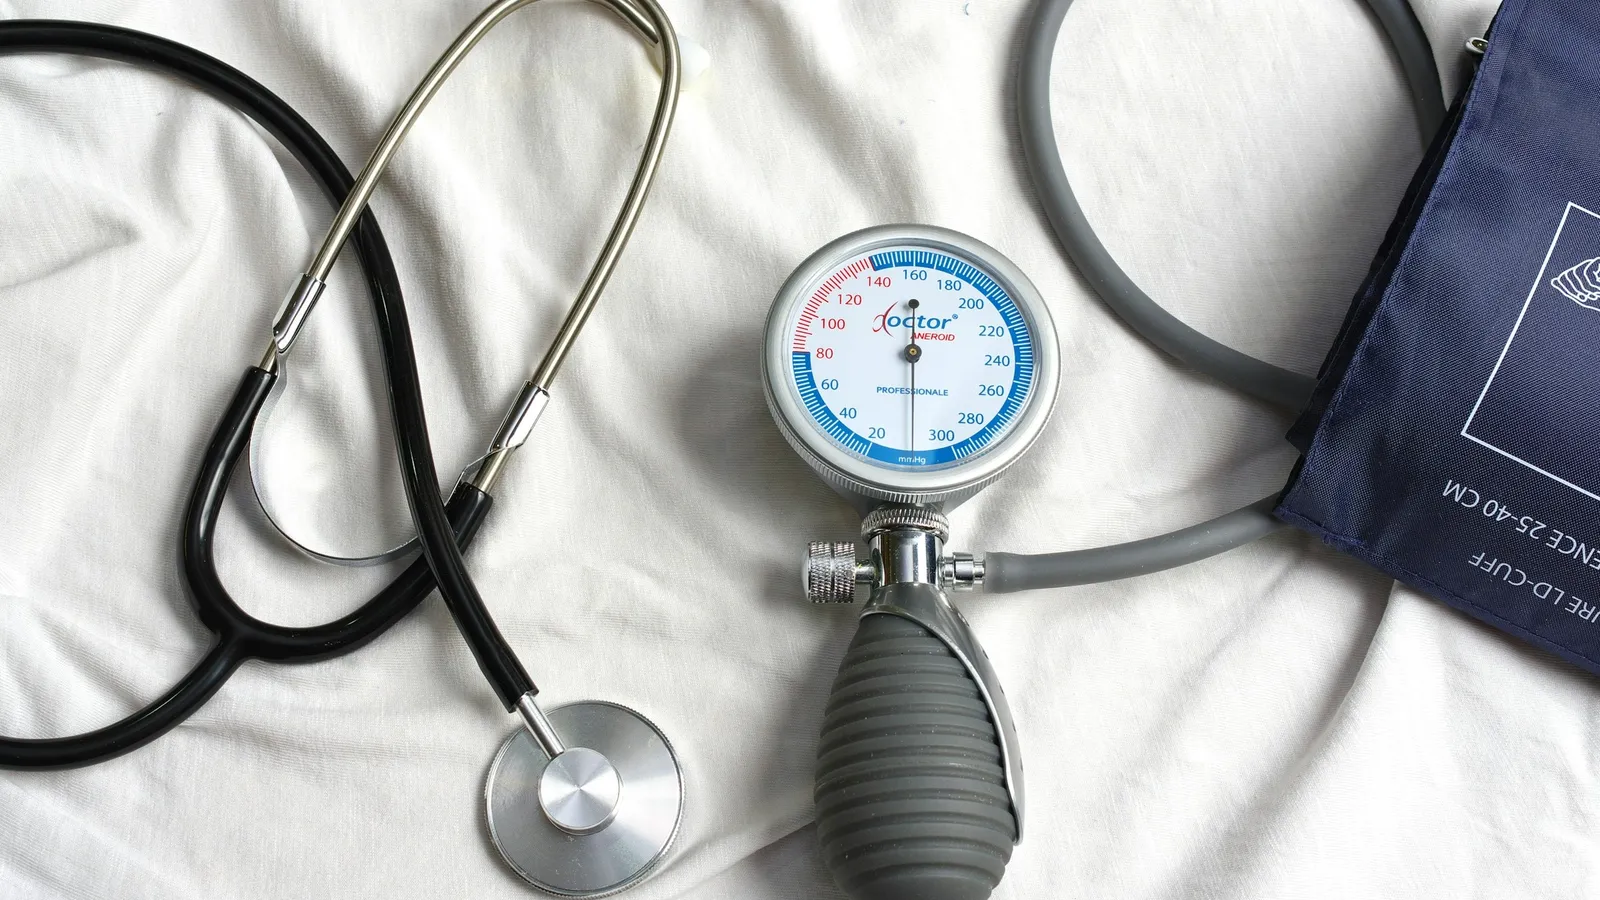
The Kidney and Blood Pressure Research tribute describes the observation. Korotkov compressed the arm with a Riva-Rocci cuff until the pulse below vanished, then slowly reduced the pressure while listening over the artery below the cuff with a stethoscope. Estañol and colleagues add that it was a child's stethoscope. A series of sounds appeared. He described four phases: a first sound, then murmurs, then a second tone, then the disappearance of all sounds. He also showed the same sounds in healthy people, not just the wounded.
He reasoned that the first sound marks systolic pressure, because that is when blood first spurts past the cuff, and proposed that the moment all sounds vanish marks diastolic pressure. In November 1905 he reported this at a conference of the Imperial Military Medical Academy, in a brief presentation titled "On the issue of the methods for measuring blood pressure". A StatPearls chapter on Korotkoff sounds gives the report's length as 281 words.
What happened next?
Others added a fifth phase, a muffling of the sound that Korotkov had missed, so textbooks now describe five phases. According to the centenary tribute, in 1939 a joint committee of the American Heart Association and the Cardiac Society of Great Britain and Ireland officially accepted his method. The American Heart Association's 2005 recommendations still call the auscultatory technique with a trained observer the method of choice in the clinic, using the first and fifth phases of the Korotkoff sounds.
Korotkov also used his method in surgery. The 2016 trauma paper reports that he examined 44 patients with war injuries to limb arteries and routinely measured an "arterial pressure index" using the sounds, a forerunner of indices still used to check blood flow in injured limbs. Estañol and colleagues add that he defended his doctoral dissertation on collateral circulation in 1910.
Worked example: reading a cuff measurement
Here is a practice case with sample numbers. A cuff is pumped to 160 mm Hg, well above the expected systolic pressure, and let down at a steady 2 mm Hg per second.
The first tapping sound is heard at 124 mm Hg. Systolic pressure = 124 mm Hg.
The sounds fade and disappear at 78 mm Hg. Diastolic pressure = 78 mm Hg.
The reading is written 124/78 mm Hg.
Time from 160 to 78 mm Hg: (160 − 78) ÷ 2 = 82 ÷ 2 = 41 seconds.
Pulse pressure, the gap between the two: 124 − 78 = 46 mm Hg.
Your NCERT Class 11 Biology chapter Body Fluids and Circulation gives 120/80 mm Hg as normal, with 120 the systolic, or pumping, pressure and 80 the diastolic, or resting, pressure. This post is about history and physiology; any question about your own readings belongs with a doctor.
Which mistakes cost marks?
Mixing up which sound gives which number. Sounds start at systolic and stop at diastolic. While the cuff is above systolic, the artery is shut and silent.
Confusing Korotkoff sounds with heart sounds. NCERT's "lub" and "dub" come from heart valves closing. Korotkoff sounds are heard over the arm artery, below the cuff.
Reversing the order. The cuff is deflated from high to low, so the systolic value is always heard first.
If the sequence of cuff pressure, artery state and sound still feels abstract, the Fermi Simulation Lab has interactive simulations for ideas easier to see than read, so you can explore how pressure and flow relate.
What can a student take from Korotkov?
Notice the unexpected. He was checking wounded limbs and heard something general.
Test beyond the first case. Confirming the sounds in healthy people made the finding universal.
Keep it short and clear. One page was enough because the method was simple and the claim was exact.
Next step: redo the worked example with sounds appearing at 132 and vanishing at 86 mm Hg, and work out the pulse pressure.